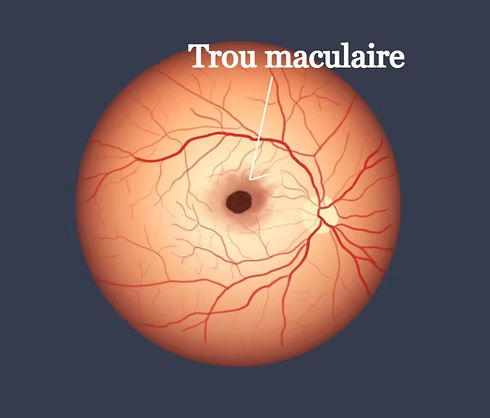
The macula is the central area of the retina, responsible for fine vision and details (reading, faces, driving). A macular hole is a small opening that forms in this area and distorts or blurs central vision. Although impressive, today it is a pathology that is very well managed surgically, with high success rates.
UnderstandWhy does a hole form?
With age, the vitreous (the transparent gel that fills the inside of the eye) gradually shrinks and detaches from the retina. In most cases, this detachment occurs without problem. But sometimes, the vitreous remains stuck to the macula and pulls on it, until it creates a real opening. This is the most common cause (we speak of an “idiopathic” hole). More rarely, a hole may appear following trauma, high myopia, or in association with another retinal disease.
SymptomsHow to recognize it?
The macular hole manifests itself by a progressive decline in central vision, straight lines that appear wavy or broken (metamorphopsia), and sometimes a dark or blurry spot in the center of the eye. Peripheral vision remains normal – it is the center of the image that is affected. These symptoms warrant rapid consultation: the sooner the hole is treated, the better the chances of visual recovery.
DiagnosisOCT, the key examination
The diagnosis is based on fundus examination, confirmed and clarified by macular OCT (optical coherence tomography). This painless and rapid examination makes it possible to precisely measure the size of the hole — an essential criterion, because the diameter directly influences the surgical strategy and the chances of success. We distinguish in particular between small holes (less than 400 microns) and larger holes, which sometimes require additional surgical techniques.
TreatmentSurgery: vitrectomy
The standard treatment is vitrectomy: the surgeon removes the vitreous responsible for the traction, then delicately prepares the edges of the hole to promote its closure. A thin natural membrane present on the surface of the retina (the internal limiting membrane) is most often removed around its perimeter, which significantly increases the chances of success. The procedure ends with the injection of a gas bubble which “buffers” the hole from the inside, while it heals.
Special casesMore complex holes
Certain holes are more difficult to close: large holes, recurrent holes after a first surgery, or those associated with severe myopia. In these situations, additional surgical techniques exist (use of biological grafts, retinal mobilization techniques) and today make it possible to obtain very good closure rates, even in cases previously considered difficult.
After the operationPosition, key to success
In the days following the operation, it is often asked to keep the head positioned downward for several days: this allows the gas bubble to press firmly on the hole and promote its definitive closure. Air travel should be avoided as long as the gas is present in the eye. Vision remains blurry for several weeks while the gas naturally resolves, then gradually improves over several months.
To remember: the earlier a macular hole is diagnosed and operated on, the better the visual prognosis. If you notice a distortion of straight lines or a decrease in central vision, consult quickly.